

The phrase “B12 injection vs tablets” describes a choice between intramuscular and oral vitamin B12 replacement, but there is no single route that is best for everyone. B12 tablets are taken by mouth and can be appropriate when oral replacement is suitable and can be taken reliably. B12 injections are given into a muscle and bypass the digestive route, which can matter when the cause of deficiency affects absorption or when the clinical situation makes intramuscular treatment more appropriate.
The most important question is therefore not whether an injection is “stronger” or “faster” than a tablet. The cause of the deficiency, symptoms, neurological or haematological risk, ability to absorb vitamin B12, adherence and follow-up all influence the choice. NICE recommends an individual approach rather than choosing treatment from symptoms or marketing claims alone.
B12 injections vs tablets at a glance
This comparison is for general education, not an individual treatment recommendation. “Tablets” means oral vitamin B12 replacement; “injections” means intramuscular vitamin B12 given as part of a clinical plan.
| Comparison point | B12 tablets / oral replacement | B12 injections / intramuscular replacement |
| Route | Swallowed; relies on an oral replacement plan and gastrointestinal absorption. | Injected into a muscle; bypasses gastrointestinal absorption for that dose. |
| When it may fit | Often considered for diet-related deficiency and other situations where oral replacement is clinically appropriate. | May be preferred or required for specific causes, persistent absorption problems or higher-risk presentations. |
| Adherence | Needs consistent dosing as advised. | Needs attendance for scheduled administration and follow-up. |
| Practical points | Avoids injections; dose/product choice and missed doses still matter. | Avoids daily oral dosing; injection-site discomfort and appointments may be disadvantages. |
| Malabsorption | High-dose oral replacement can be used in some malabsorption situations under clinical guidance. | Often considered when absorption is persistently impaired; lifelong for some irreversible causes under NICE guidance. |
| Monitoring | Response, adherence and the underlying cause may need review. | Response, injection schedule and the underlying cause may need review. |
| Duration | May be temporary or long-term, depending on cause. | May be a course, maintenance or lifelong, depending on cause. |
The cause of B12 deficiency changes the treatment choice
Vitamin B12 deficiency can develop for different reasons. Some people do not get enough B12 from food, while others cannot absorb it normally because of autoimmune gastritis, stomach or bowel surgery, gastrointestinal disease or another continuing problem. Medicines can also contribute to low B12 in some people. Identifying the likely cause helps determine whether diet, oral replacement, intramuscular treatment or further investigation is appropriate.
Symptoms alone cannot reliably identify the cause. Tiredness, poor concentration, weakness, pins and needles, numbness and balance problems can occur with B12 deficiency, but they can also have other explanations. A treatment decision should therefore consider symptoms alongside risk factors, previous results, medical history and any established diagnosis.
When oral B12 replacement may be appropriate
When a low intake of vitamin B12 is the likely cause, oral replacement may be a practical option. NICE advises considering oral vitamin B12 replacement for deficiency suspected to be diet-related. Dietary advice may also be useful, particularly for people following vegan, vegetarian or otherwise restricted diets.
Oral treatment still needs an appropriate product, dose, duration and review plan. Taking a low-dose supplement occasionally is not the same as following a clinically selected replacement regimen. Adherence matters because missed doses or an unsuitable dose can reduce the effectiveness of oral treatment.
When malabsorption changes the decision
Malabsorption means the body is not absorbing vitamin B12 normally through the gastrointestinal tract. The severity and permanence of that problem matter. For vitamin B12 deficiency caused by autoimmune gastritis, or after total gastrectomy or complete terminal ileal resection, NICE recommends lifelong intramuscular vitamin B12 replacement.
For other confirmed or suspected malabsorption, NICE says vitamin B12 replacement should be offered and intramuscular treatment should be considered instead of oral replacement. NICE also allows oral treatment in some malabsorption situations and specifies a dose of at least 1 mg a day when that route is used. The prescriber or responsible clinician determines the individual plan.
An injection bypasses gastrointestinal absorption for that dose. That can make it a dependable route when absorption is persistently impaired, but it does not mean injections are universally more powerful than tablets. The clinical advantage comes from matching the route to the cause.
Adherence and practical differences also matter
Tablets can be convenient because they do not require an injection appointment, but they depend on taking the treatment as advised. Injections remove the need for daily oral dosing, but they require attendance for administration and may cause temporary injection-site discomfort. Neither route is automatically easier for every person.
Practical factors should be considered alongside clinical need. A person who struggles to take tablets consistently may need a different plan, while someone who can take oral treatment reliably may prefer to avoid injections when the oral route is clinically suitable.
Neurological symptoms need prompt assessment
Vitamin B12 deficiency can affect the nervous system. New or worsening numbness, pins and needles, balance or walking problems, marked weakness, memory or cognitive changes, or vision changes deserve prompt medical assessment. NICE advises that vitamin B12 replacement should not be delayed while waiting for test results when a clinician suspects megaloblastic anaemia with neurological symptoms.
This is an urgent clinical exception, not a reason to self-diagnose or arrange repeated injections without assessment. Contact a GP promptly for concerning neurological symptoms, use NHS 111 when urgent advice is needed and the situation is not life-threatening, and call 999 for a medical emergency.
Testing before starting or changing treatment
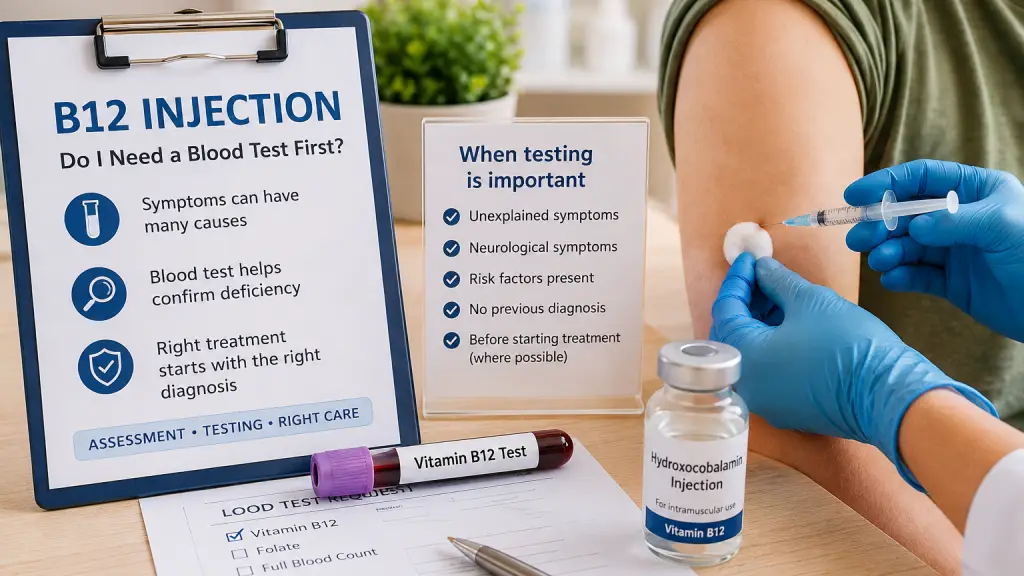
Where the clinical situation allows, diagnostic blood samples are normally taken before vitamin B12 replacement starts because tablets and injections can alter measured B12 levels and make later results harder to interpret. Testing can also help identify whether another cause of symptoms needs attention.
If you have not been diagnosed, your symptoms are unexplained, or you are considering changing an existing B12 plan, read our guide on whether a blood test is needed before a B12 injection. Bring recent results, a diagnosis or treatment plan, and a list of medicines and supplements to any clinical review.
Monitoring and judging whether treatment is working
Monitoring is not only about seeing whether a B12 number rises. The responsible clinician may consider symptoms, blood-count changes, neurological findings, adherence, the underlying cause and whether treatment is being taken or administered as planned. Follow-up also helps identify people whose symptoms are not improving because another condition may be contributing.
Do not increase injection frequency, stop prescribed injections or switch to tablets without advice from the clinician responsible for your care. A route that was appropriate at diagnosis may need review if circumstances change, but the decision should be made using the cause, response and current clinical picture.
Do injections work faster or better than tablets?
Not necessarily. Intramuscular treatment makes vitamin B12 available without relying on gastrointestinal absorption, but the time it takes for symptoms to improve depends on the severity and duration of deficiency, the symptoms involved and whether another condition is contributing. A rapid feeling of extra energy is not a reliable measure of treatment success.
The evidence-based B12 injection benefits come from correcting or preventing deficiency when injection treatment is clinically appropriate. They should not be presented as a guaranteed boost to energy, mood, concentration or general wellbeing. Oral replacement can also be effective when it is the appropriate route and is taken correctly.
Side effects and medicine-specific considerations
Hydroxocobalamin is the injectable vitamin B12 medicine commonly used in the UK. Possible effects include pain, swelling or itching at the injection site, as well as nausea, diarrhoea, headache, dizziness or flushing. Serious allergic reactions are uncommon but require urgent medical help.
Oral vitamin B12 avoids an injection, but the exact product and dose still matter. Tell a pharmacist, GP or other healthcare professional about all prescribed medicines, over-the-counter products, vitamins and supplements you use, as well as allergies and previous reactions. Do not assume that several overlapping B12 products are safer or more effective.
Questions to discuss with a pharmacist or GP
Useful questions include: What is the likely cause of the deficiency? Is oral replacement suitable for that cause? Is there evidence of malabsorption? Are neurological symptoms present? What dose, duration and follow-up are required? How will response be reviewed? Could medicines, surgery or another condition be contributing? These questions keep the decision focused on the diagnosis rather than on whether injections or tablets sound more convenient.
If you are considering injections in Luton
If you already have relevant blood results, a diagnosis or an established treatment plan, you can discuss the appropriate replacement route with our pharmacist. If injection treatment is being considered, information about B12 injections at our Biscot Road pharmacy explains the local private service. Every appointment is subject to pharmacist suitability assessment, and consultation does not guarantee that an injection will be given. Testing, GP review or another route may be recommended instead.
Conclusion
B12 injections and tablets are both ways of replacing vitamin B12; they are not competing wellness products. Oral replacement can be appropriate for diet-related deficiency and other clinically selected situations. Intramuscular replacement can be preferred or required when absorption is persistently impaired, when specific surgery has removed the normal absorption pathway, or when the clinical risk and treatment plan support that route.
The safest choice comes from understanding why B12 is low, assessing symptoms and risk factors, testing when appropriate and following an individual treatment plan. Discuss the appropriate replacement route with a pharmacist, GP or the clinician responsible for your care rather than switching treatment on your own.
Author and clinical review
Written by the Biscot Pharmacy Editorial Team.
Medically reviewed by Faisal Shafiq, Superintendent Pharmacist (GPhC 2067224).
Last reviewed: 1 August 2026.
Frequently asked questions
Are B12 injections better than tablets?
Not automatically. Tablets can be appropriate when oral replacement can meet a person’s needs and can be taken reliably. Injections may be more appropriate for certain causes of deficiency, persistent absorption problems or higher-risk clinical situations. The correct route depends on assessment.
Can B12 tablets work if I have malabsorption?
Sometimes. NICE allows oral vitamin B12 replacement in some confirmed or suspected malabsorption situations and specifies at least 1 mg a day when that route is used. Intramuscular treatment should also be considered, and some causes require lifelong injections.
Can diet-related B12 deficiency be treated with tablets?
Yes. Oral vitamin B12 is commonly considered when diet is the suspected cause. Dietary advice and follow-up may also be needed. Injections can still be appropriate in selected circumstances, such as significant clinical risk or serious concerns about reliable oral treatment.
When are B12 injections more likely to be used?
Injections are more likely to be used when intramuscular replacement better fits the cause or clinical risk, including some persistent malabsorption problems. NICE recommends lifelong intramuscular replacement for deficiency caused by autoimmune gastritis and after total gastrectomy or complete terminal ileal resection.
Should I have a blood test before changing B12 treatment?
Diagnostic blood samples are usually taken before replacement starts when the clinical situation allows because treatment can affect results. If you already have a diagnosis or treatment plan, speak to the responsible clinician before changing route, dose or frequency.
Can I switch from injections to tablets?
Do not switch a prescribed treatment plan without professional advice. Whether a change is appropriate depends on the cause of deficiency, absorption, symptoms, previous response, adherence and the follow-up plan.
Disclaimer
This page provides general information and does not diagnose vitamin B12 deficiency or recommend an individual treatment route. Symptoms can have other causes and may require blood tests, GP assessment or specialist care. Do not start, stop, switch or change prescribed vitamin B12 treatment without advice from the clinician responsible for your care. Pharmacy service eligibility, availability and treatment remain subject to assessment.



 the prescription app


